

Should I Save the Tooth or Replace It With an Implant? A Washington, DC Decision Guide
Told a cracked, decayed or root-canal-treated tooth should come out? What makes a tooth worth saving, what makes it hopeless, why an implant is not automatically the safer choice, and the questions to ask before extraction.
Practice clinician: Gerald M. Marlin, DMD, MSD, prosthodontist, Elite Prosthetic Dentistry, Friendship Heights, Washington, DC. Last updated .
A cracked tooth, a tooth with decay under an old crown, or a root canal treated tooth that has become sore again raises the same question: is it worth saving, or should it come out and be replaced with an implant? Both answers are sometimes right. The mistake is to treat either one as automatic. This guide explains what makes a tooth worth keeping, what makes it hopeless, why an implant is a replacement rather than an upgrade, and what to ask before anything irreversible is done.

Patients bring this question to Elite Prosthetic Dentistry from several directions. A general dentist has found decay under a crown and recommended extraction and an implant. An endodontist has said the root canal failed. A tooth has fractured and the patient has been told it cannot be rebuilt. Or the patient has read that implants are more predictable and wonders whether to skip the repair altogether. Each case is decided the same way: by the condition of that tooth, not by a general preference for teeth or for implants.
A Tooth Is Worth Saving When These Things Are True
- The root is intact. No vertical fracture, and no resorption that has hollowed the root from inside or outside.
- Enough tooth remains above the bone to hold a crown. A crown needs sound tooth structure to grip; crown lengthening can expose more when the margin sits too close to the bone, but there is a limit.
- The bone around the root is adequate. A tooth with moderate bone loss that is stable and cleanable can be kept; a tooth that moves because its support is gone cannot.
- Any infection can be resolved. Root canal treatment, retreatment, or surgery at the root tip can resolve most infections when the root is sound and the canal can be reached.
- The restoration can be designed to protect it. A tooth that has lost structure needs a crown designed for the forces it will carry, and a bite that does not overload it.
When these conditions hold, saving the tooth preserves the ligament, bone and sensation that an implant does not replace. The patient keeps a natural tooth, and the implant option remains available later if it is ever needed.
A Tooth Is Hopeless When These Things Are True
- A vertical root fracture. Once a root is split along its length, bacteria track into the fracture and the tooth cannot be sealed. It should be removed.
- Decay or resorption below the bone. When the damage extends where a restoration cannot reach and crown lengthening cannot expose it, the tooth cannot be restored predictably.
- Too little tooth left. A root with almost nothing above the bone, even after crown lengthening, cannot support a crown that will last.
- Advanced bone loss. When periodontal disease has removed most of the support and the tooth is mobile, keeping it risks the neighboring bone.
- An infection that cannot be resolved. A root canal that has failed retreatment, a canal that cannot be reached, or a persistent infection after surgery.
These findings should be visible on the examination, the X-rays or the CBCT scan, and the clinician should be able to show them to you. A recommendation to extract that rests on a general statement (“it is a weak tooth,” “implants are more predictable”) rather than a specific finding deserves a second look before the tooth is gone.
Why an Implant Is a Replacement, Not an Upgrade
Implants are an excellent solution for a missing tooth. They are not a better version of a natural tooth. An implant has no ligament, so it does not provide the sensory feedback or shock absorption of a tooth. It is attached directly to bone and is more vulnerable to overload in a heavy bite. The gum around it is less resistant to inflammation than the gum around a tooth. And an implant can fail, develop bone loss or need its crown replaced, just as a tooth can.
None of this argues against implants. It argues against removing a savable tooth on the assumption that the implant will be trouble-free. The right comparison is the prognosis of this tooth, saved, against the prognosis of an implant in this site, in this bone, in this bite. Sometimes the implant wins that comparison clearly. Sometimes the tooth does.
What the Evaluation Should Give You
- The specific finding for the tooth, with the imaging that shows it.
- Whether retreatment, crown lengthening, a new post and core, or a redesigned crown was considered, and why each was kept or ruled out.
- A prognosis for the tooth if it is saved: good, guarded or poor, and the reason.
- If replacement is recommended: whether the bone will support an implant in the correct position, whether grafting would be needed, whether a bridge is a reasonable alternative, and what the plan is if an implant does not integrate.
- How the bite affects either choice, since a tooth or an implant placed into an overloaded bite will fail either way.
A patient who leaves with those answers can make the decision. A patient who leaves with a quote for an implant and no finding for the tooth cannot.
How Elite Prosthetic Dentistry Approaches the Decision
The practice provides both answers, which is why its advice is not shaped by what it is able to do. Dr. Gerald M. Marlin evaluates the tooth on examination and imaging, including a CBCT scan where the finding depends on it, and classifies it as savable with a stated prognosis or hopeless with a stated reason. Where the tooth can be kept, the practice coordinates endodontic treatment or retreatment with specialist colleagues where needed, arranges crown lengthening where the margin requires it, and designs the post, core and crown in its on-site laboratory. Where the tooth cannot be kept, Dr. Marlin plans, surgically places and restores the implant in the same office, with the final crown designed before the surgery so the implant is placed where the tooth needs it.
Dr. Marlin has placed more than 3,900 dental implants and holds 9 U.S. patents in dental implant restoration methodology. He is also a prosthodontist whose specialty is restoring teeth, and the documented cases below include several in which the recommended extraction did not happen.
When Another Setting Fits Better
A tooth whose only problem is a failed root canal, with sound structure and no restorative complication, is well served by an endodontist for retreatment, with the crown made by the patient’s own dentist. A tooth with a clear, uncontroversial reason for extraction in a patient with a trusted general dentist and surgical colleague does not need a specialty evaluation. Active periodontal disease across the mouth should be treated before any single-tooth decision is made. The evaluation will say which applies.
Documented Cases That Show the Decision
Teeth that were saved:
- Two upper front teeth saved after another dentist and surgeon recommended extraction and implants: custom posts and crowns on intact roots.
- A root canal treated tooth with decay and resorption, recommended for an implant, resolved without the implant: the evaluation found a bite and restoration problem rather than a single failing tooth.
- Recurrent decay beneath mismatched crowns treated with root canals and buildups before a customized bridge.
- Loose, failing crowns and hidden decay: one hopeless tooth removed, strategic teeth preserved and both arches rebuilt.
Teeth that could not be saved, and what replaced them:
- A front tooth broken at the gum line in a bike accident, replaced with a graft, a guided implant and a custom crown.
- A front tooth lost to childhood trauma, rebuilt with bone grafting and a single implant.
- Failing lateral incisor implants replaced with custom zirconia bridges, a reminder that an implant is not the only replacement and not always possible.
More cases are organized in the second opinion and implant reconstruction success story hubs.
Related Decision Guides
- When to seek a second opinion before dental implants, extraction or major treatment
- Replacing a missing front tooth: implant, bridge, or saving the tooth
- Keep your teeth or replace them? Selective implants vs. full-arch extraction
- Who should place your dental implant in Washington, DC?
- When should old crowns and bridges be replaced?
Request an Evaluation of the Tooth
If you have been told a tooth should come out, request an appointment or call (202) 244-2101 before it is extracted. Bring the X-rays and the written recommendation; the evaluation will give you a finding for the tooth and a prognosis for both choices.
Your Best Smile Is Within Reach
Request a specialist consultation with Dr. Marlin to discuss your situation and the most appropriate path forward.
Frequently Asked Questions
Is an implant more reliable than saving a tooth with a root canal and crown?
Not as a rule. A well-treated tooth with sound root structure, adequate bone and a properly designed crown can serve for decades, and it keeps the ligament, bone and sensation that no implant reproduces. Implants are an excellent replacement for a tooth that cannot be kept; they are not an upgrade over a tooth that can. Both can fail, and both need maintenance. The comparison has to be made for the specific tooth, from its records.
When is a tooth truly hopeless?
The common findings are a vertical root fracture, decay or resorption that extends below the bone where a restoration cannot seal it, too little remaining tooth above the bone to hold a crown even after crown lengthening, advanced bone loss leaving the root without support, or a root canal infection that has failed retreatment or cannot be retreated. Each of these should be visible on the examination or the imaging and explained to you.
My tooth has already had a root canal. Does that make it a candidate for extraction?
No. A root canal treated tooth that develops a problem can often be retreated, treated surgically at the root tip, or rebuilt with a new post and crown. Previous treatment is part of the history, not a verdict. What matters is the remaining tooth structure, whether the root is intact, and whether the infection can be resolved.
If the tooth is saved, how long will it last?
No honest answer gives a number without the records. The prognosis depends on how much tooth remains, the quality of the root canal treatment, the design and fit of the crown, the bite it lives in and the patient's hygiene. The evaluation should tell you whether the prognosis for that tooth is good, guarded or poor, and why, so that you can weigh it against the alternative.
What should I ask before agreeing to an extraction?
What is the specific finding that makes this tooth unsavable, and can I see it on the X-ray or scan? Was retreatment, crown lengthening or a new post and crown considered, and why was it ruled out? What is the prognosis if the tooth is saved versus replaced? If an implant is proposed, is there enough bone, who will place and restore it, and what is the plan if the implant does not integrate? A clinician who has evaluated the tooth can answer all of these.
Related Patient Success Stories
Explore similar patient success stories demonstrating our expertise in advanced prosthetic dentistry.
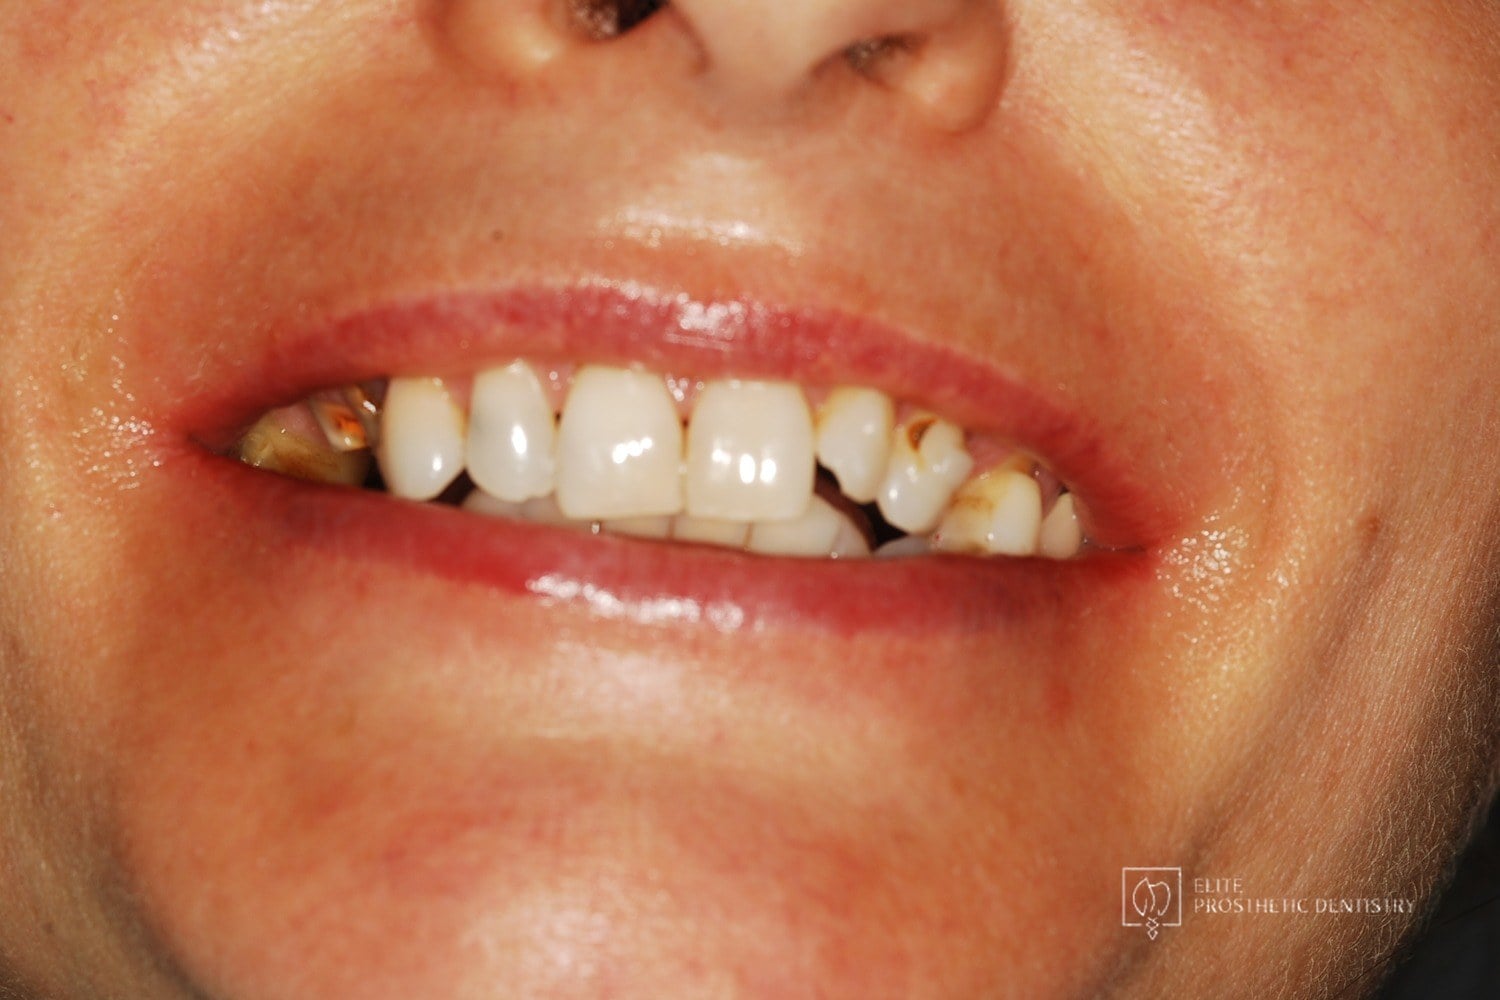 Before
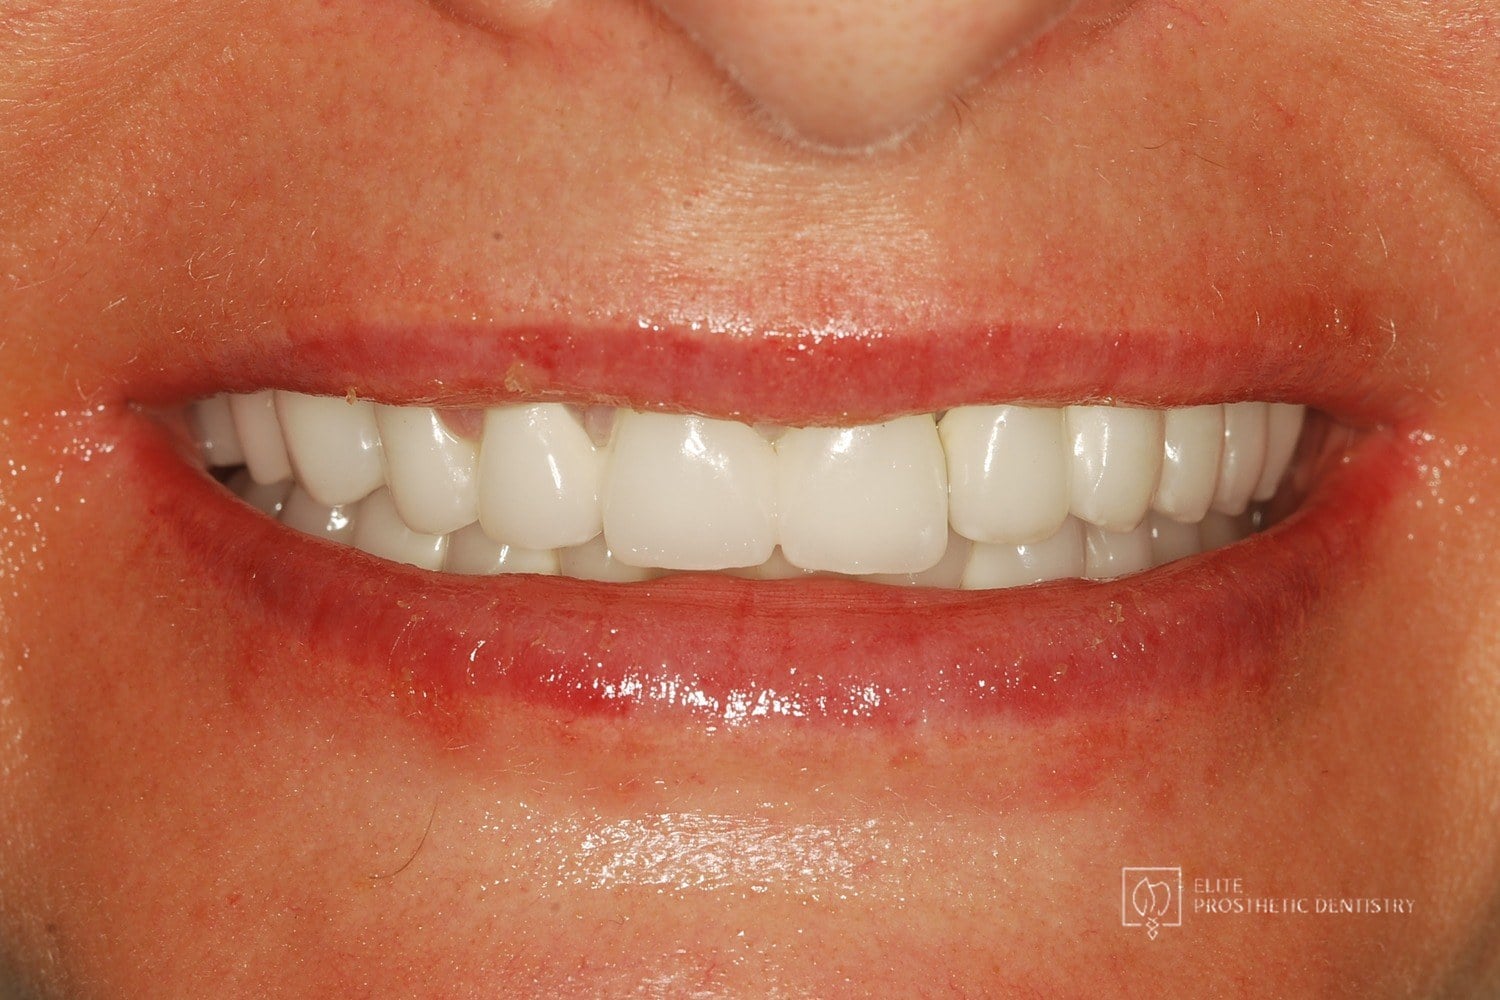 After
How Aging, Failing Dentistry Was Replaced with a Coordinated Full-Mouth Implant and Crown Reconstruction
The patient presented with throbbing upper-molar pain, long-standing infections, multiple root canals and unfinished prior treatment, generalized sensitivity, and several hopeless teeth.
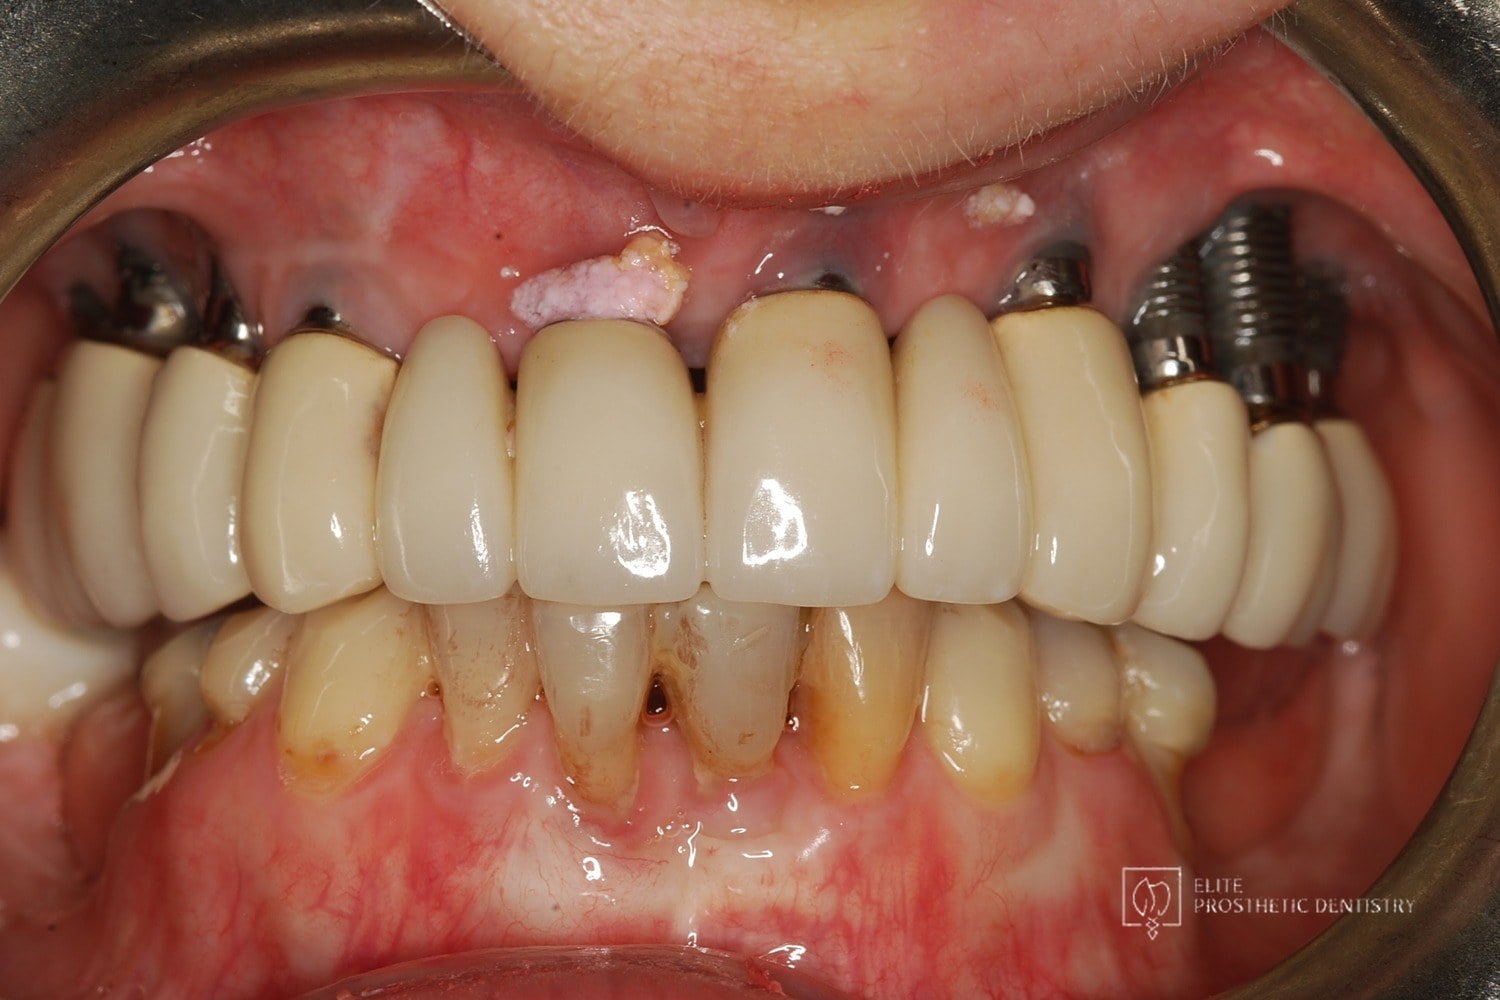 Before
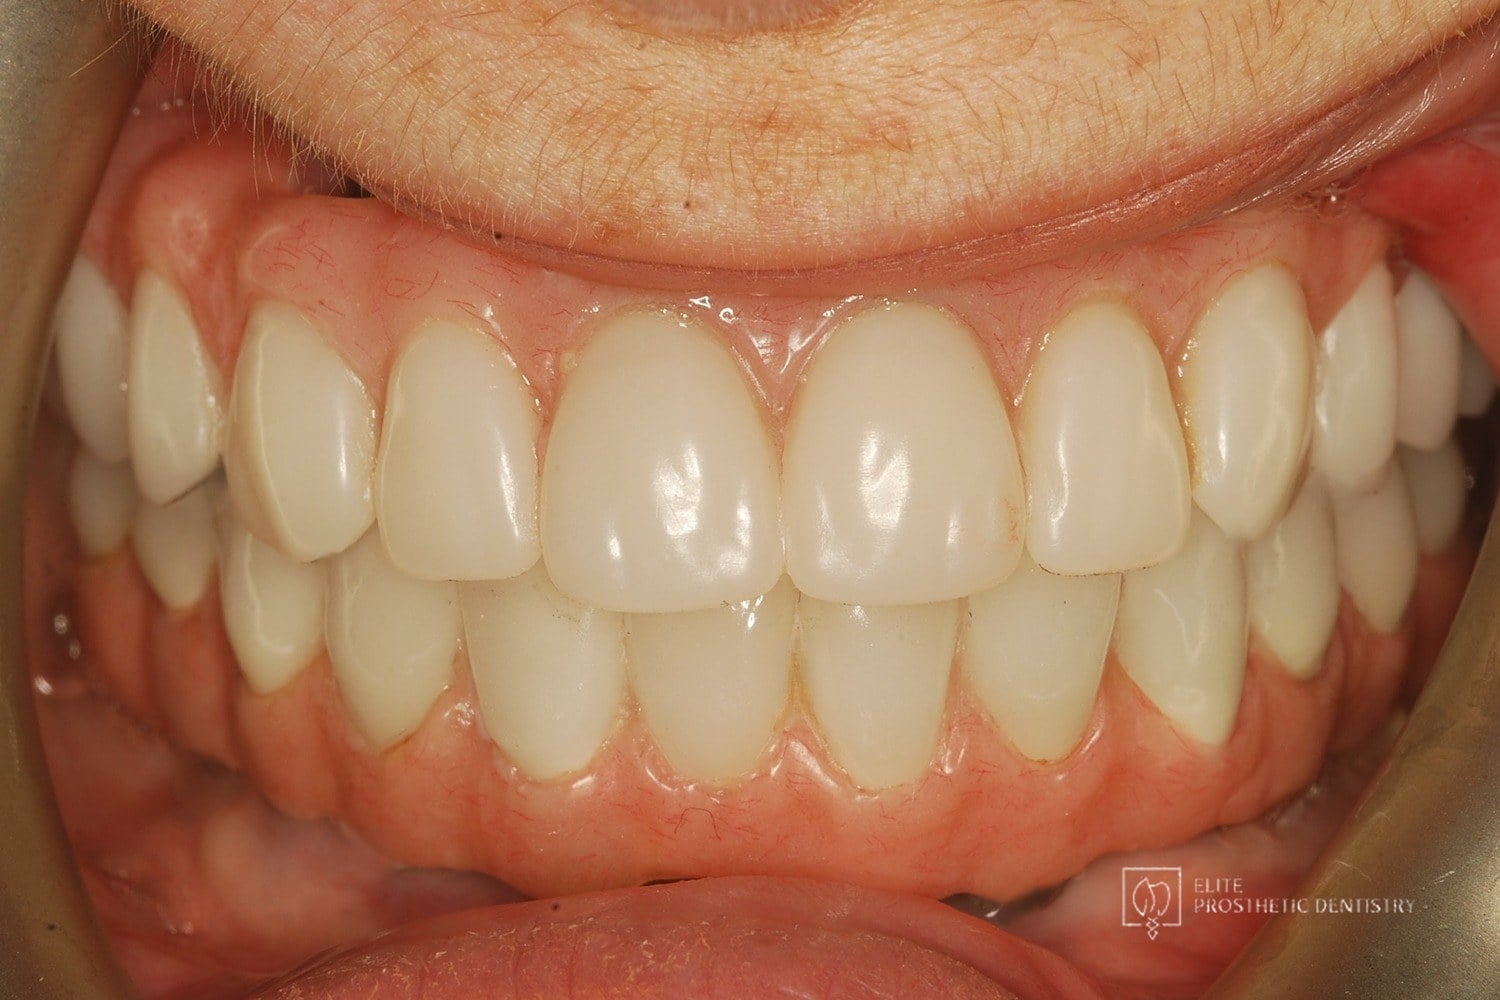 After
How Failing Implants and Severe Bone Loss Were Rebuilt Into a Stable Full-Arch Implant Reconstruction
The patient presented with significant complications from previously placed implants, severe bone loss, failing posterior implants, and an unesthetic full-arch bridge. Both arches required full reconstruction, with the upper arch showing the most advanced bone loss and instability.
 Before
 After
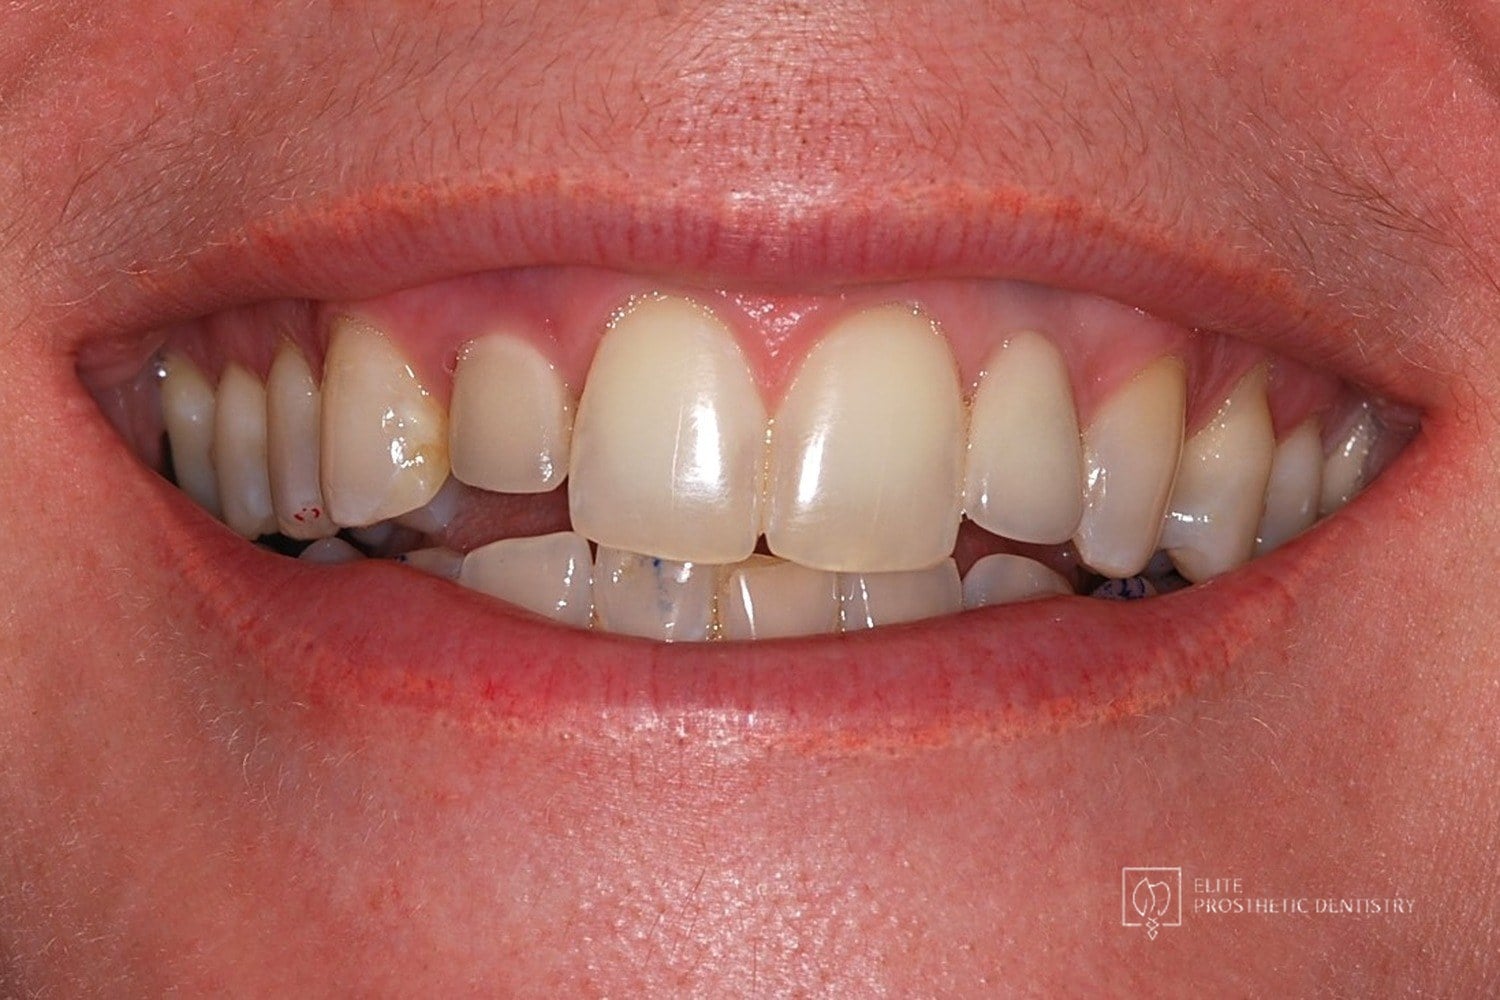
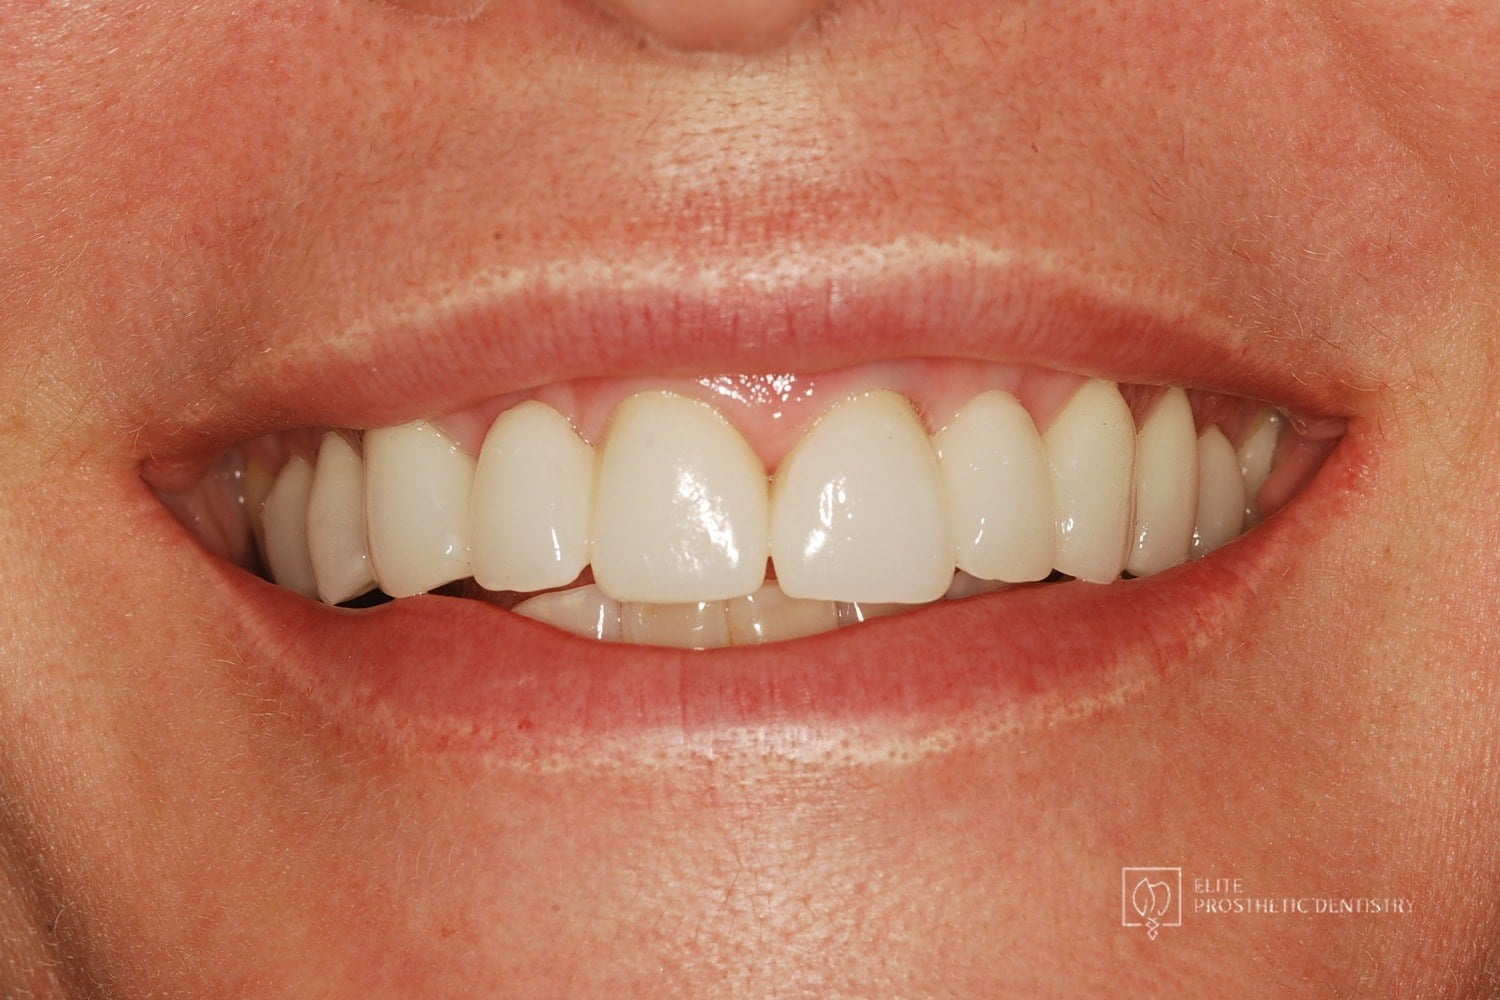
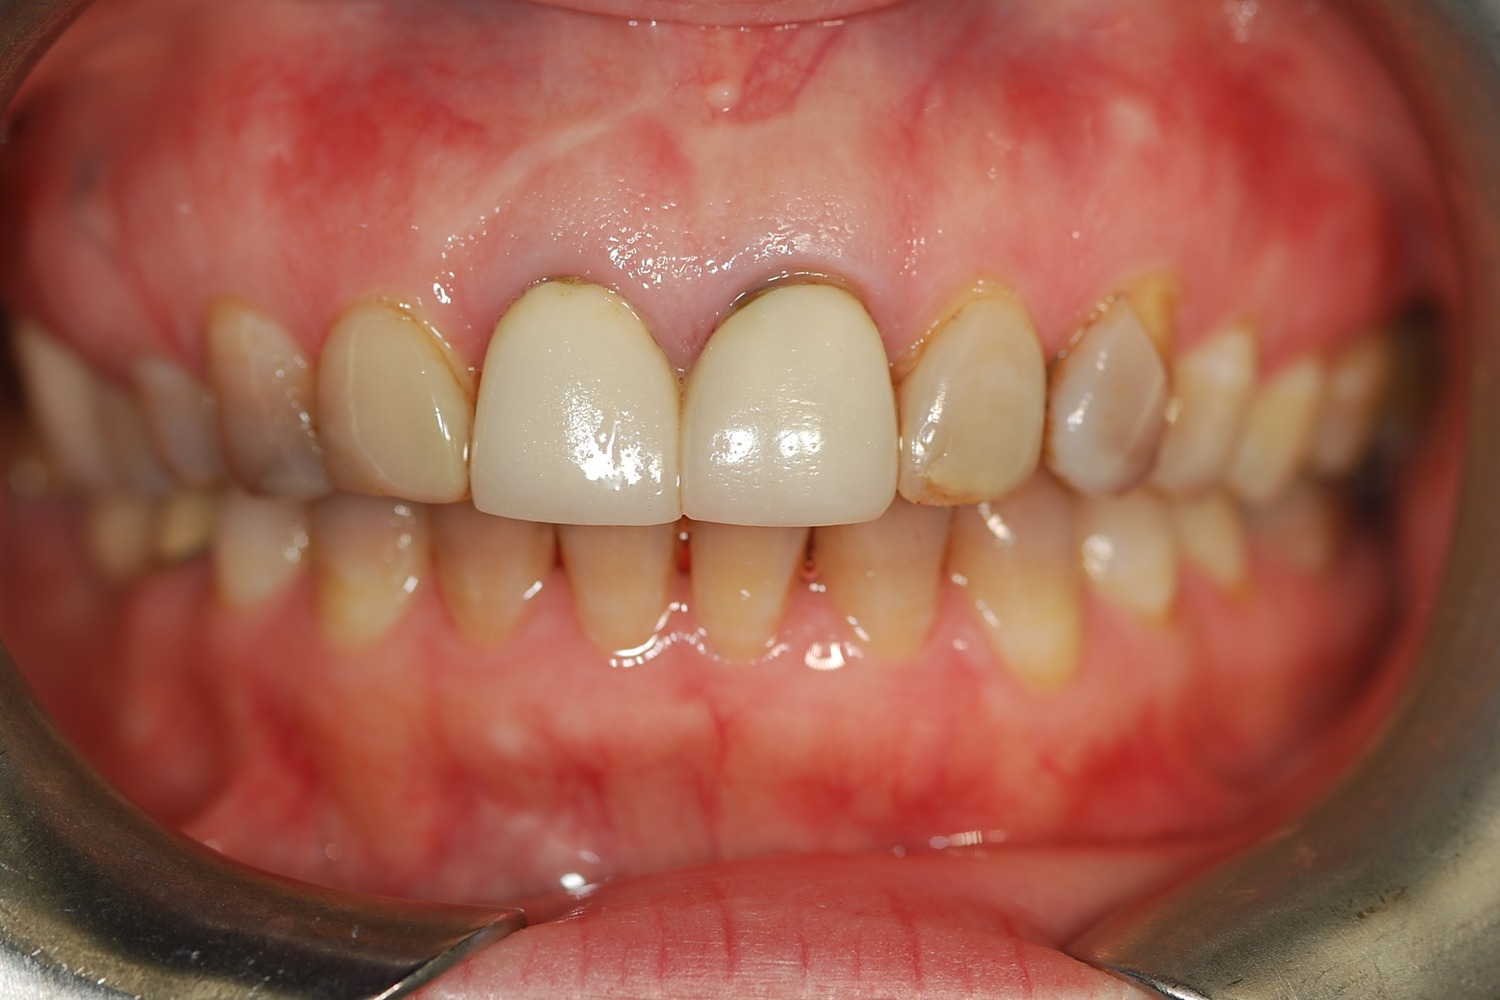
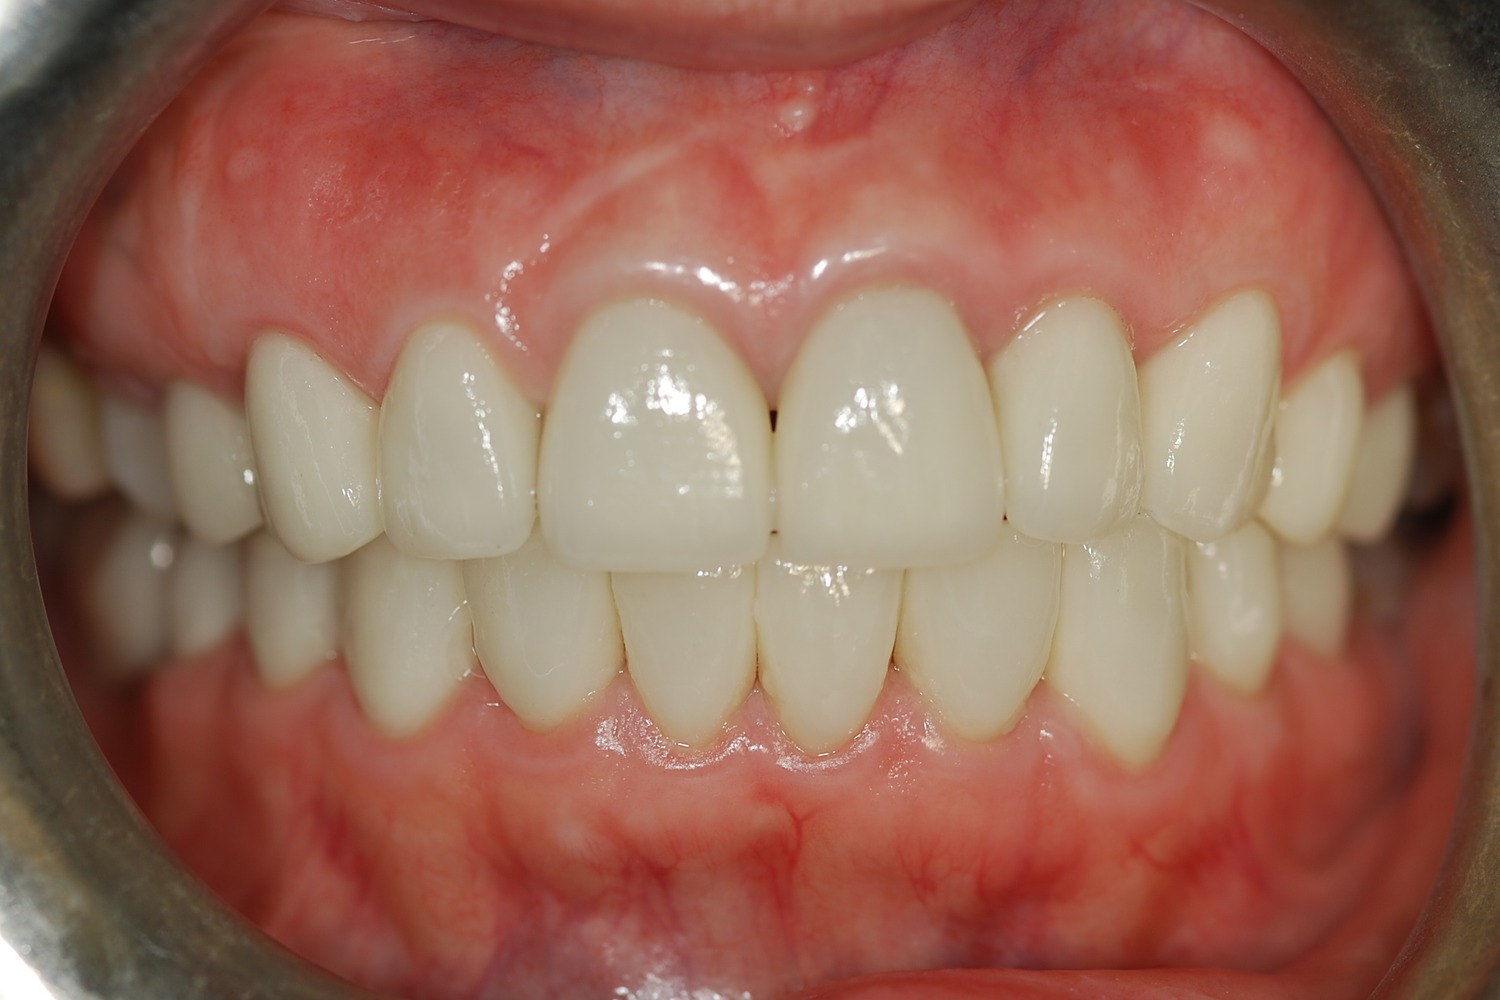
How Failing Lateral Incisor Implants Were Replaced with Custom Zirconia Bridges After Severe Bone Loss Made Replacement Implants Impossible
Comprehensive examination including CBCT imaging revealed significant bone loss surrounding implants that were placed outside the buccal plate, most likely due to placement without a CBCT-generated surgical guide. The implants were determined non-salvageable, and the alveolar ridge was too narrow to support replacement implants without extensive reconstruction.
 Before
 After
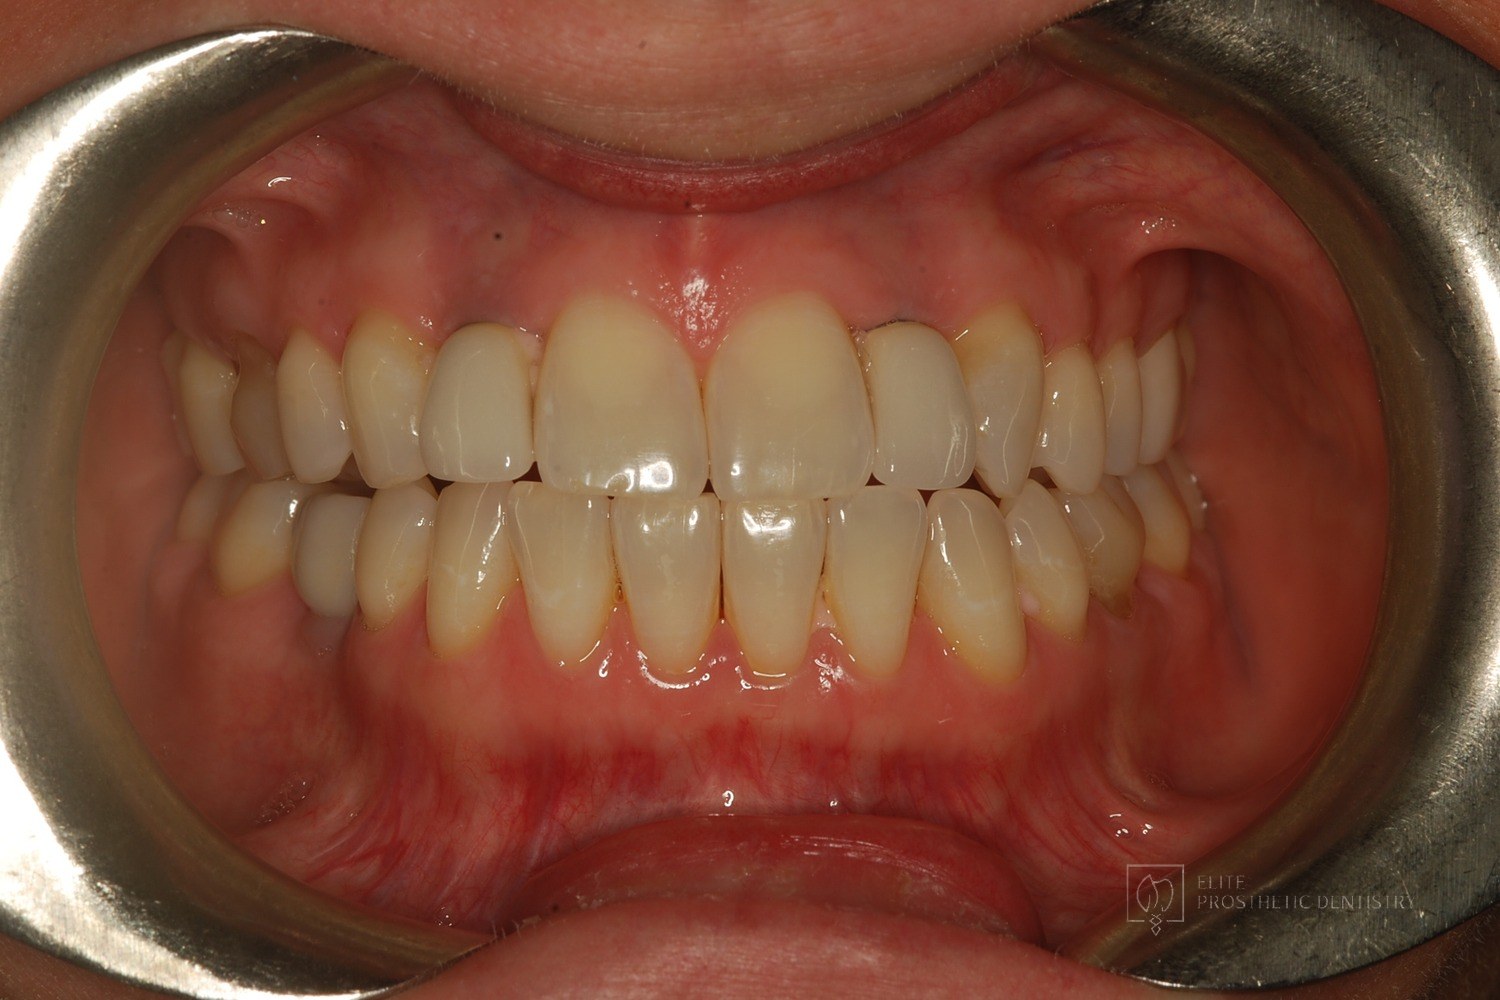
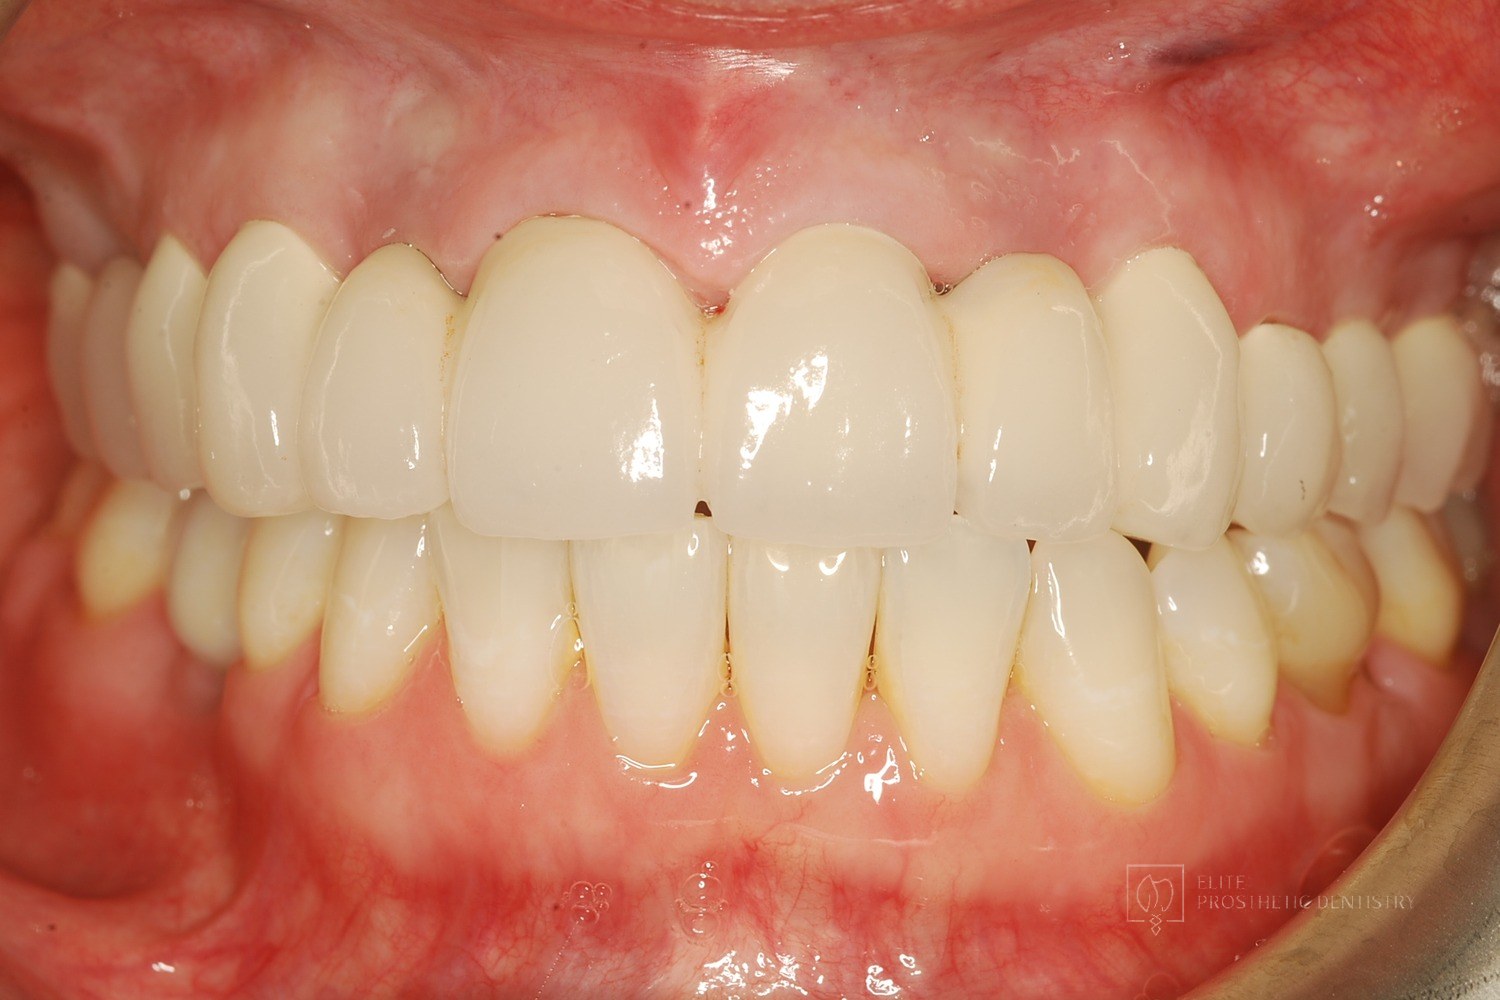
How Aging, Opaque Restorations Were Replaced with Customized Ceramic Restorations Designed for Long-Term Natural Esthetics
The existing restorations appeared opaque, worn, and unnatural over time, affecting both confidence and overall smile harmony.
 Before
 After
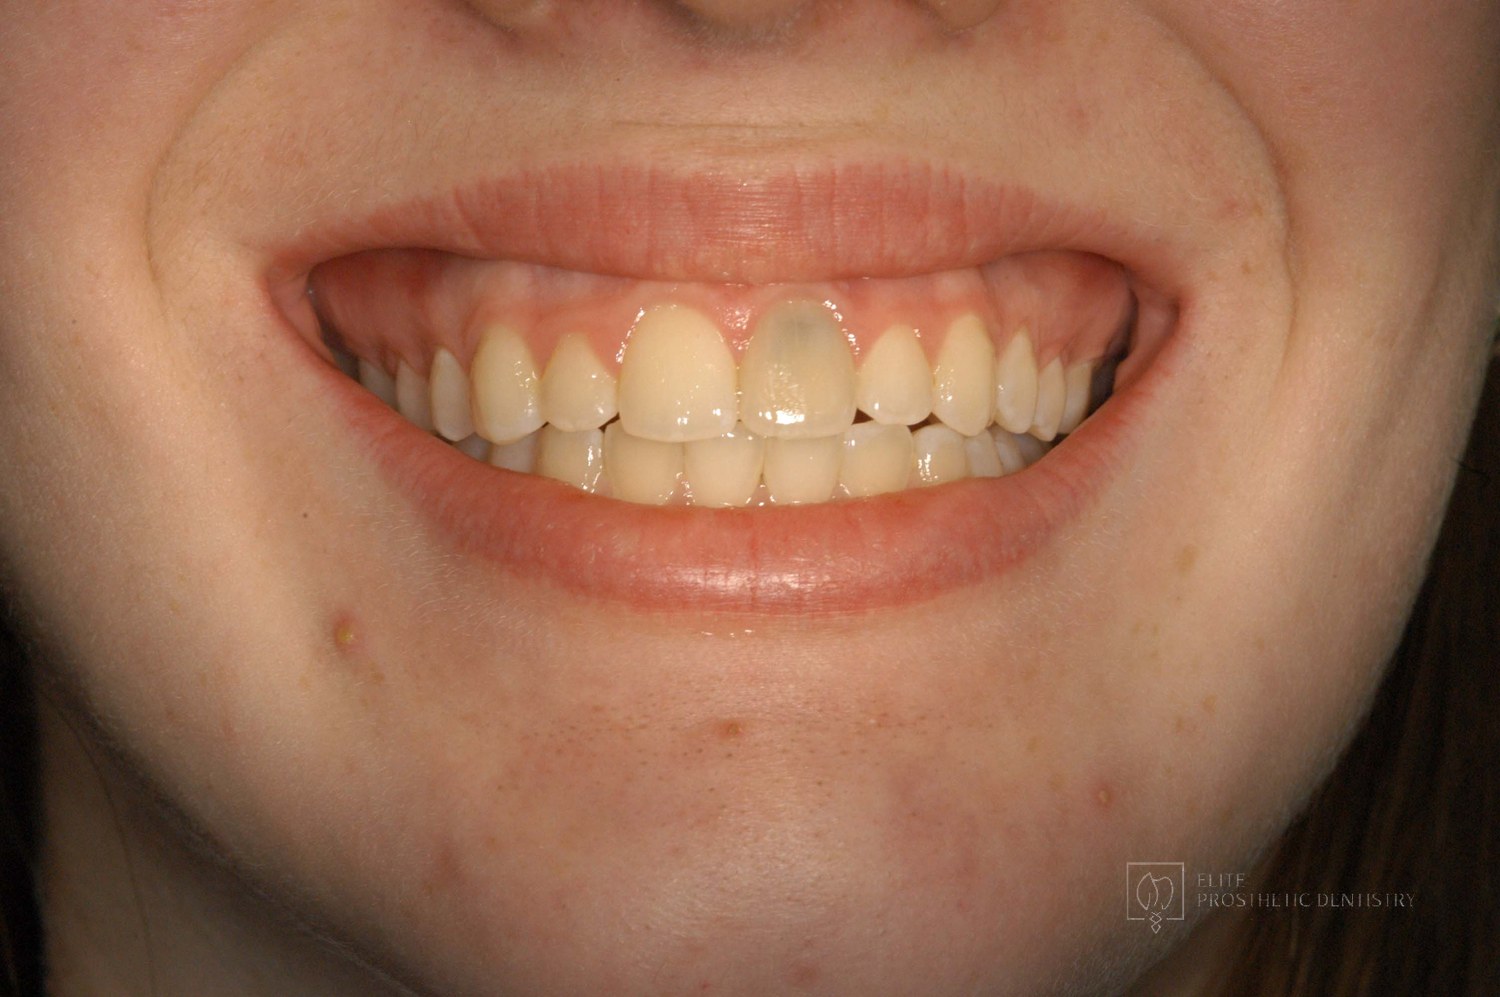
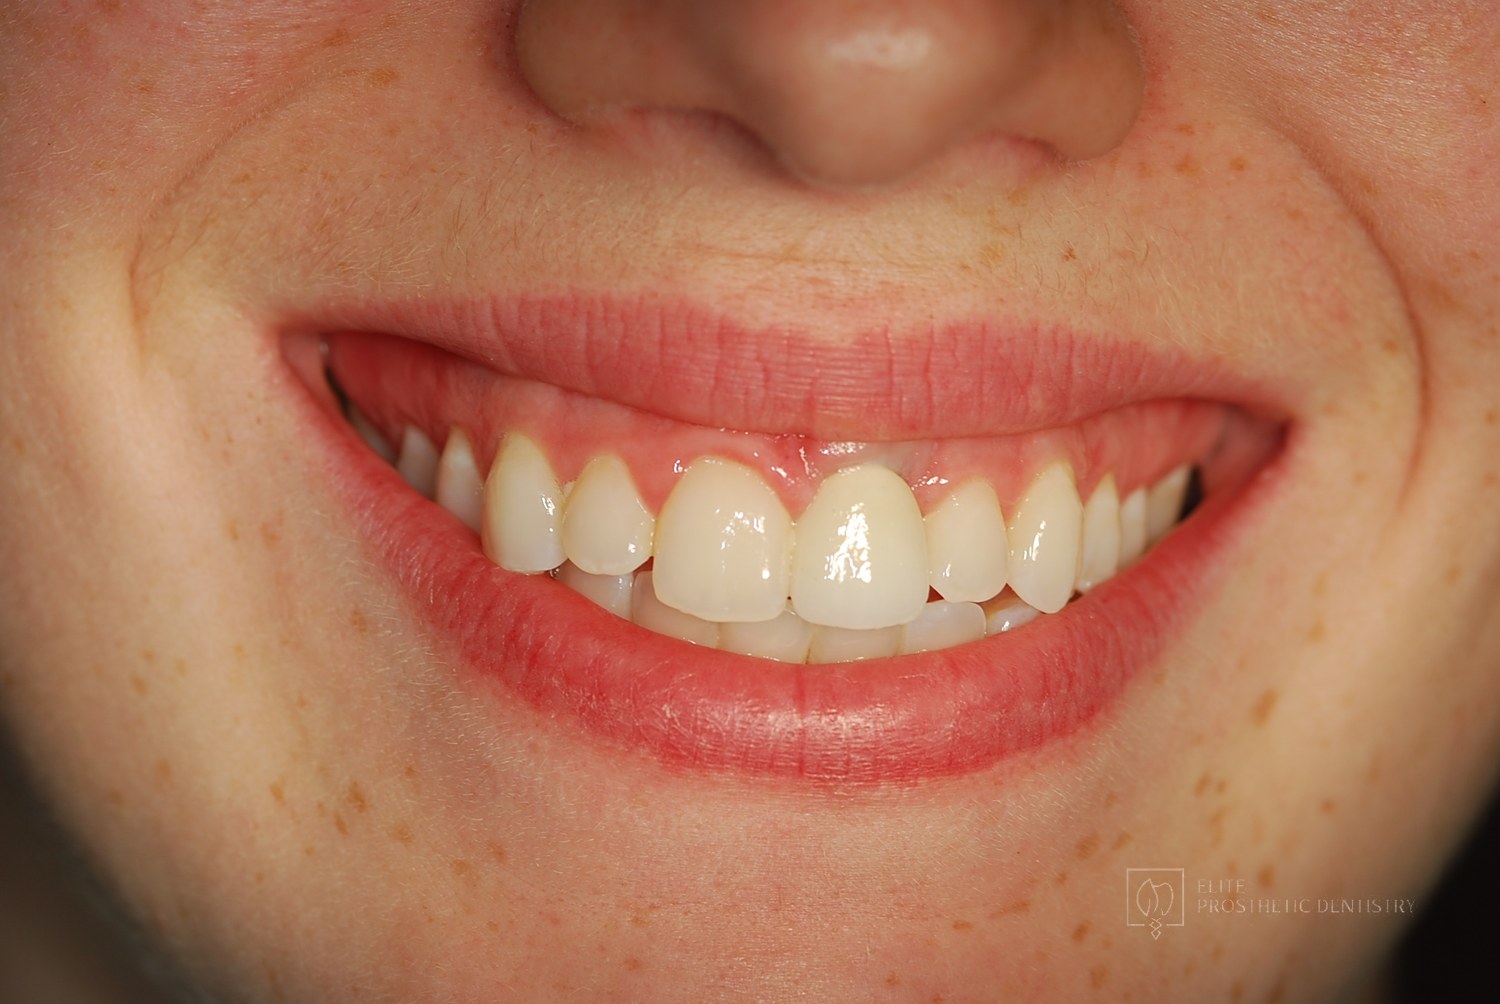
How Older Implant Crowns Were Redesigned for a Better Bite and More Natural Appearance
The patient came in after years of living with implant-supported crowns placed more than twenty years earlier that no longer looked or functioned well. CBCT evaluation, reviewed with a radiologist colleague, showed the implants had been placed too far to the buccal in very thin bone and could not support a healthy long-term restoration.
 Before
 After
How a Front Tooth Lost to Childhood Trauma Was Rebuilt with Bone Grafting and a Long-Lasting Implant
A teenager was referred by her father after earlier trauma left her upper left front tooth slowly failing from root resorption. She was still growing, so an immediate implant was the wrong move. The tooth had to be maintained to buy time, then replaced correctly once she reached skeletal maturity.
Related Articles
Deepen your knowledge with additional insights on this topic.
 Dental Implants
If a Single Front Tooth Is Replaced with an Implant, Can It Look Natural?
Yes. See the four steps, with real case photos, that make a single front tooth implant indistinguishable from the natural tooth beside it. Washington, DC.
 Dental Implants
What Is Precision Implant Placement (PIP)?
Precision Implant Placement plans each implant virtually on a CBCT scan, then delivers it with a custom surgical guide. See the three steps with real images.
 Dental Implants
What Is the Ideal Surgical Guide for Precision Implant Placement?
Not all surgical guides are equal. The gold standard is CBCT-based: planned virtually in 3D, 3D printed, and seated on your teeth. A DC prosthodontist explains.
 Dental Implants
When Should an Implant Not Be Done?
Healthy roots, thin bone, steep bony angles: a DC prosthodontist shows a real case where refusing implants was the right call, and what was done instead.
 Dental Implants
What Is Staged Implant Therapy?
Staged implant therapy replaces failing teeth in phases while you keep fixed teeth the entire time. A DC prosthodontist walks through a real case in stages.
 Dental Implants
The Four Types of Dental Implants: Which One Is Right for You?
Endosteal, subperiosteal, zygomatic, and mini implants each solve a different problem. A DC prosthodontist explains the four types and who each one fits.
Ready to Transform Your Smile?
With 40+ years of experience and 3,900+ dental implants placed, Dr. Marlin and the team deliver dentistry planned to last. Request a specialist consultation.